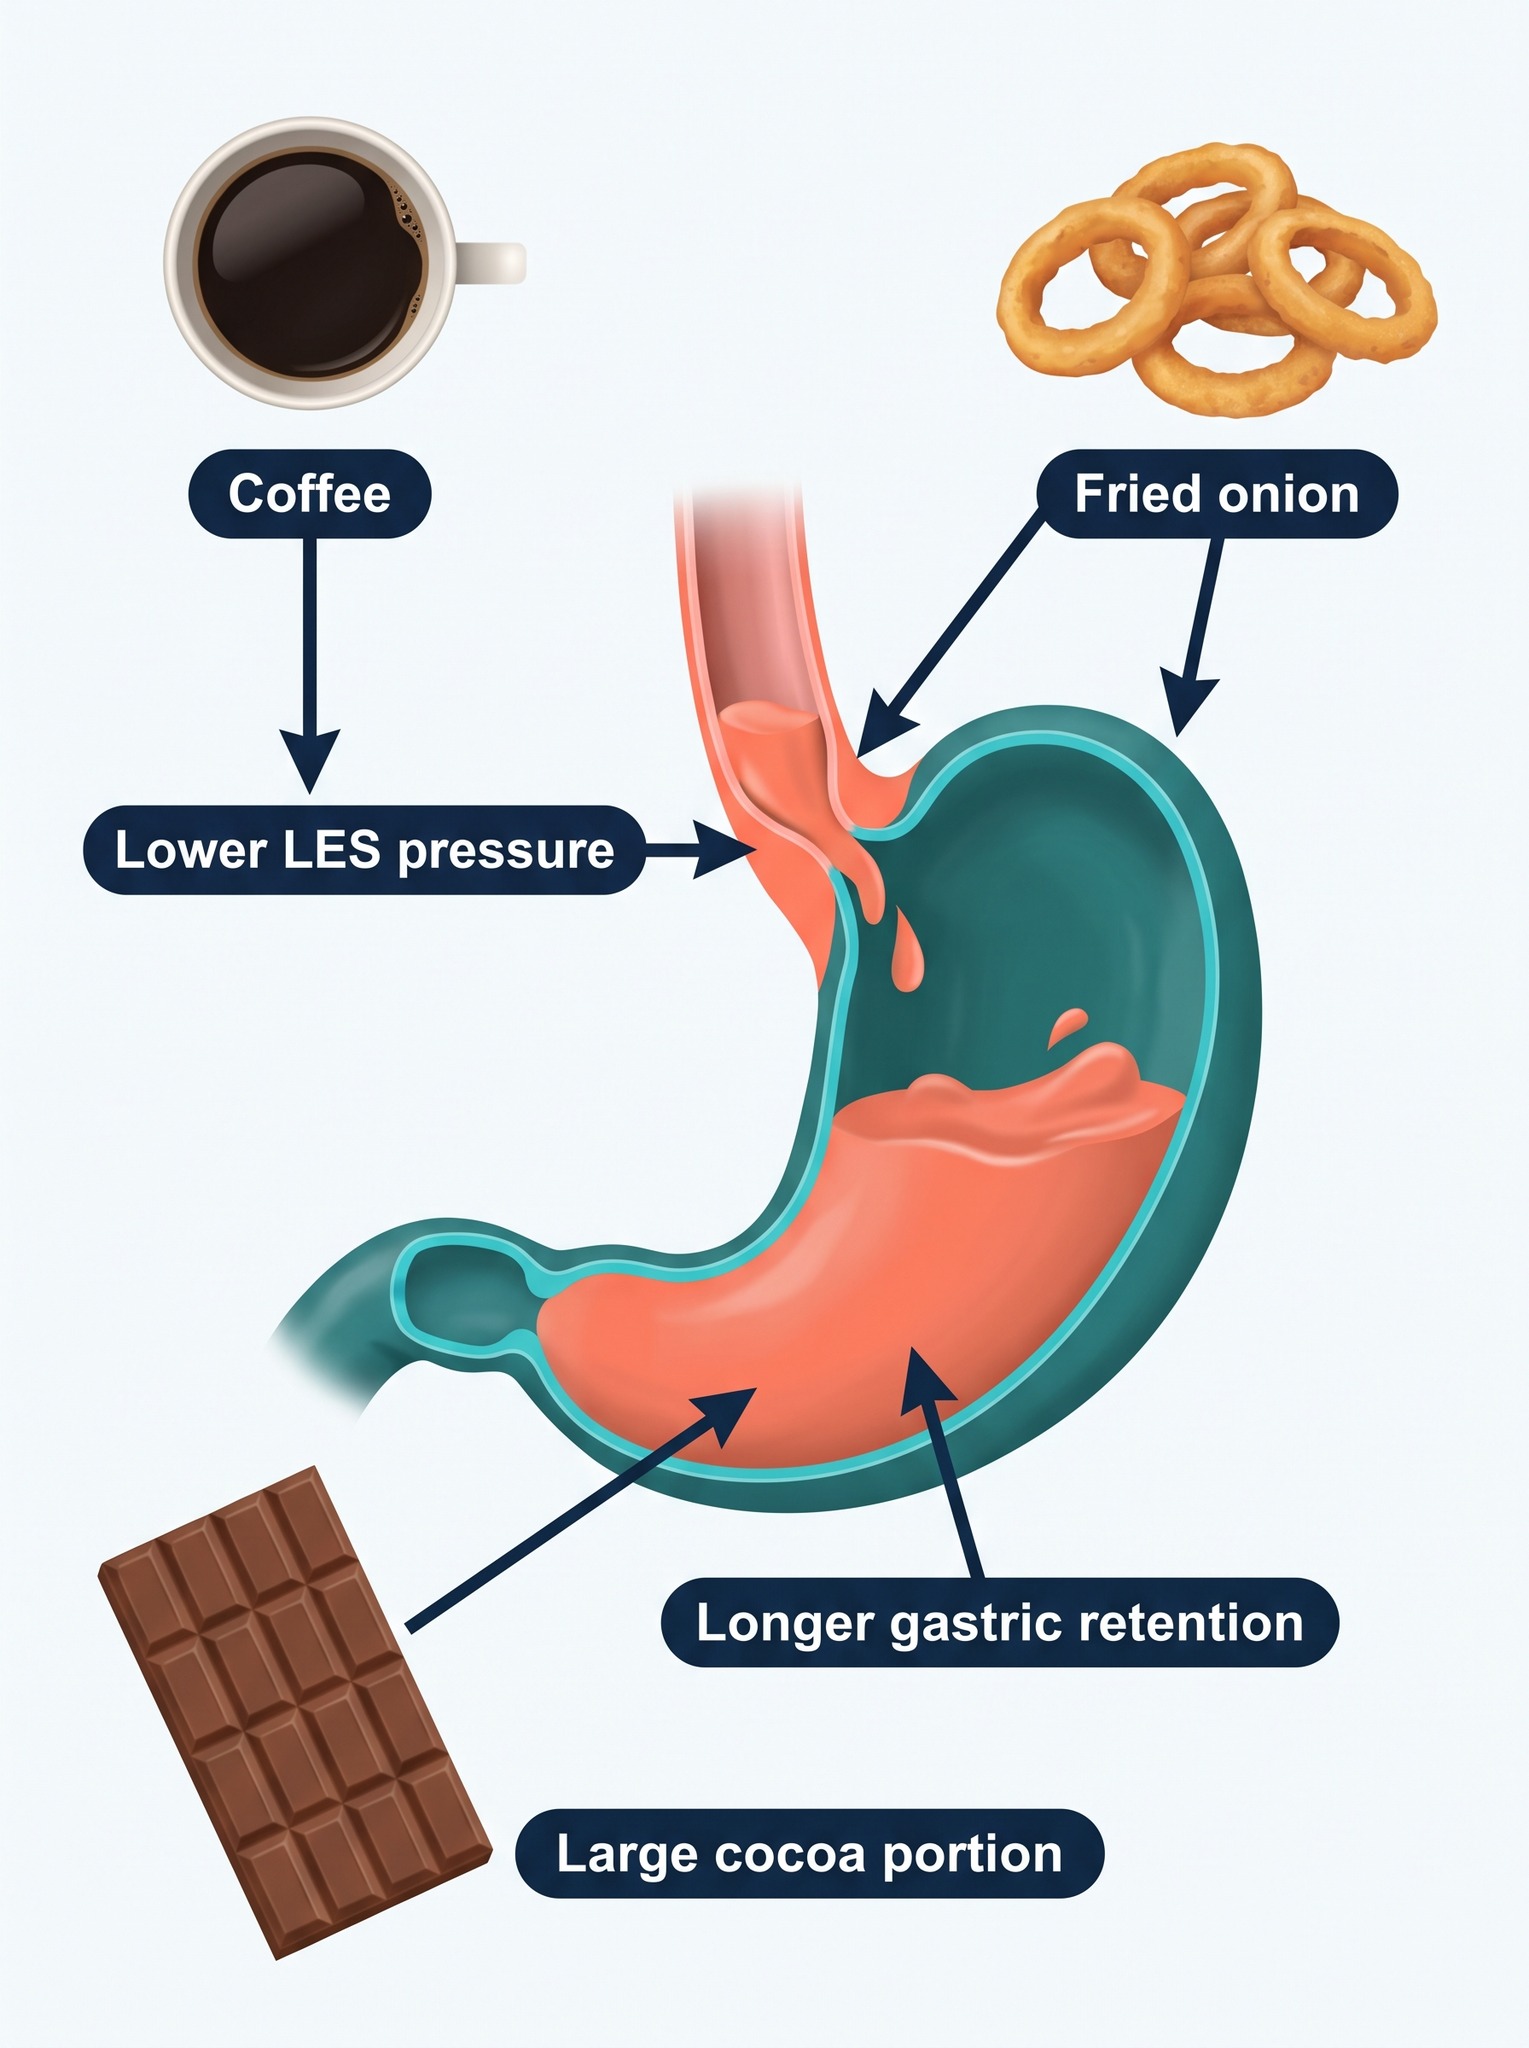
A delayed sleep schedule shifts gastric work into the biological night, when solid food empties more slowly and recumbency removes gravity from oesophageal clearance. The connection between sleeping late and stomach pain becomes stronger when late-night eating, disturbed digestion and lack of sleep occur together. For Rondo, stomach pain at night or the following morning tracks a 9 p.m. meal and a 12:30 a.m. bedtime, while coffee, fried onion and large cocoa portions repeatedly worsen the same pattern.
Understand the pattern behind the symptoms
IBSyncrasy explains how daily habits, motility and gut signalling can keep digestive symptoms active after routine investigations look reassuring. Buy IBSyncrasyHow did Rondo’s stomach pain become a recurring pattern?
Rondo, 41 years old
Rondo is 41, weighs 75 kg and has a BMI of 21.9 kg/m². His upper digestive symptoms began in 2015 during a period of intense stress and frequent nighttime eating. Reflux came first. Over time, the pattern expanded into epigastric pain, indigestion, post-meal fullness and early satiety.
Dinner at 9 p.m. and sleep at 12:30 a.m.
His final meal commonly includes bread, cheese and chicken at 9 p.m., followed by sleep around 12:30 a.m. Symptoms can appear after the meal or the next morning. Fast eating, daily sweets, pastries and dairy products add more gastric load to the same evening window.
Coffee, fried onion and cocoa reproduce the discomfort
Coffee, fried onion and a large amount of cocoa repeatedly precede pain, burning or a heavy stomach. Milk, alcohol and oversized meals also worsen symptoms. The pattern follows both food composition and quantity, which points toward reflux physiology, gastric retention and heightened sensitivity working together.
Clearance weakens when he lies down
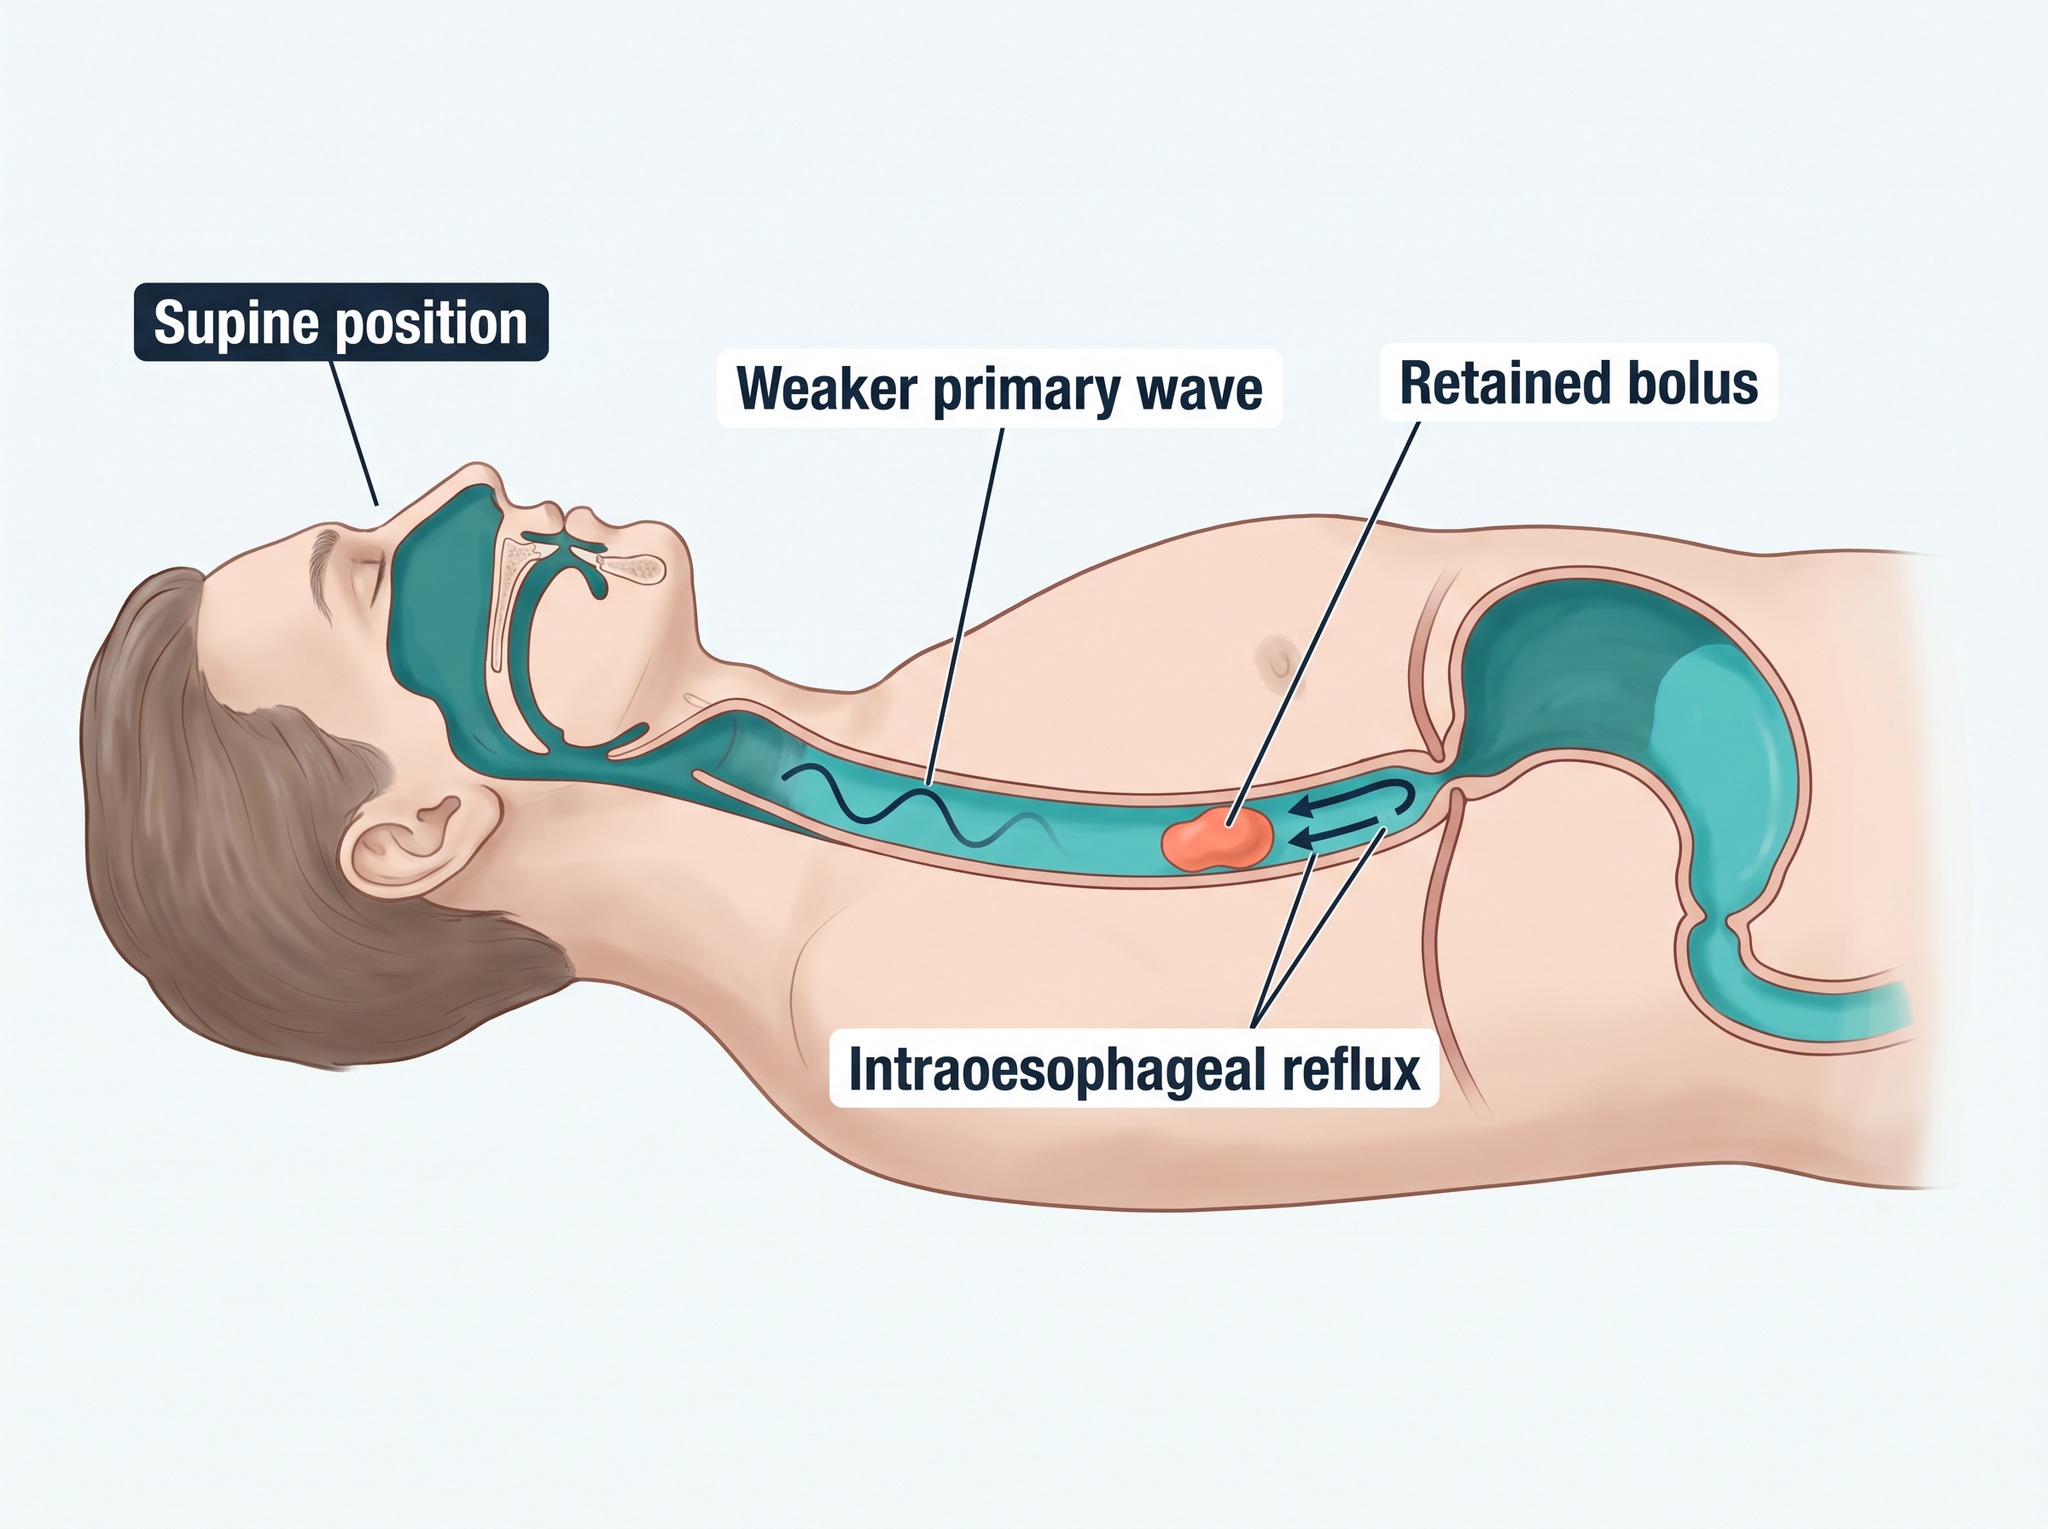
Videofluoroscopy found normal oesophageal motility while seated and in the oblique prone position. In the supine position, the primary peristaltic wave became weaker, part of the bolus remained inside the oesophagus and intraoesophageal reflux appeared. Residue was also recorded after yoghurt boluses.
The tissue improved while the symptoms continued
In 2022, endoscopy showed mild lower oesophageal sphincter insufficiency, grade 1 oesophagitis, excess gastric fluid, antral microerosions and an inflamed pyloric region. By January 2026, the oesophagus, stomach and duodenum looked normal, yet dyspepsia, epigastric heaviness, early satiety and recurrent reflux symptoms continued with only partial relief from omeprazole.
Why can sleeping late and stomach pain become linked?
Gastric emptying, acid secretion, gut hormones and mucosal cell renewal follow daily rhythms. In a human study, an identical solid meal took 53.6% longer to empty at 8 p.m. than at 8 a.m.[1] Therefore, the same dinner creates a different mechanical burden when it moves toward the biological night.
Evening solid-meal emptying takes longer
Goo et al., Gastroenterology, 1987. Evening emptying time was 53.6% longer.[1]
What changes after the meal moves into the night?
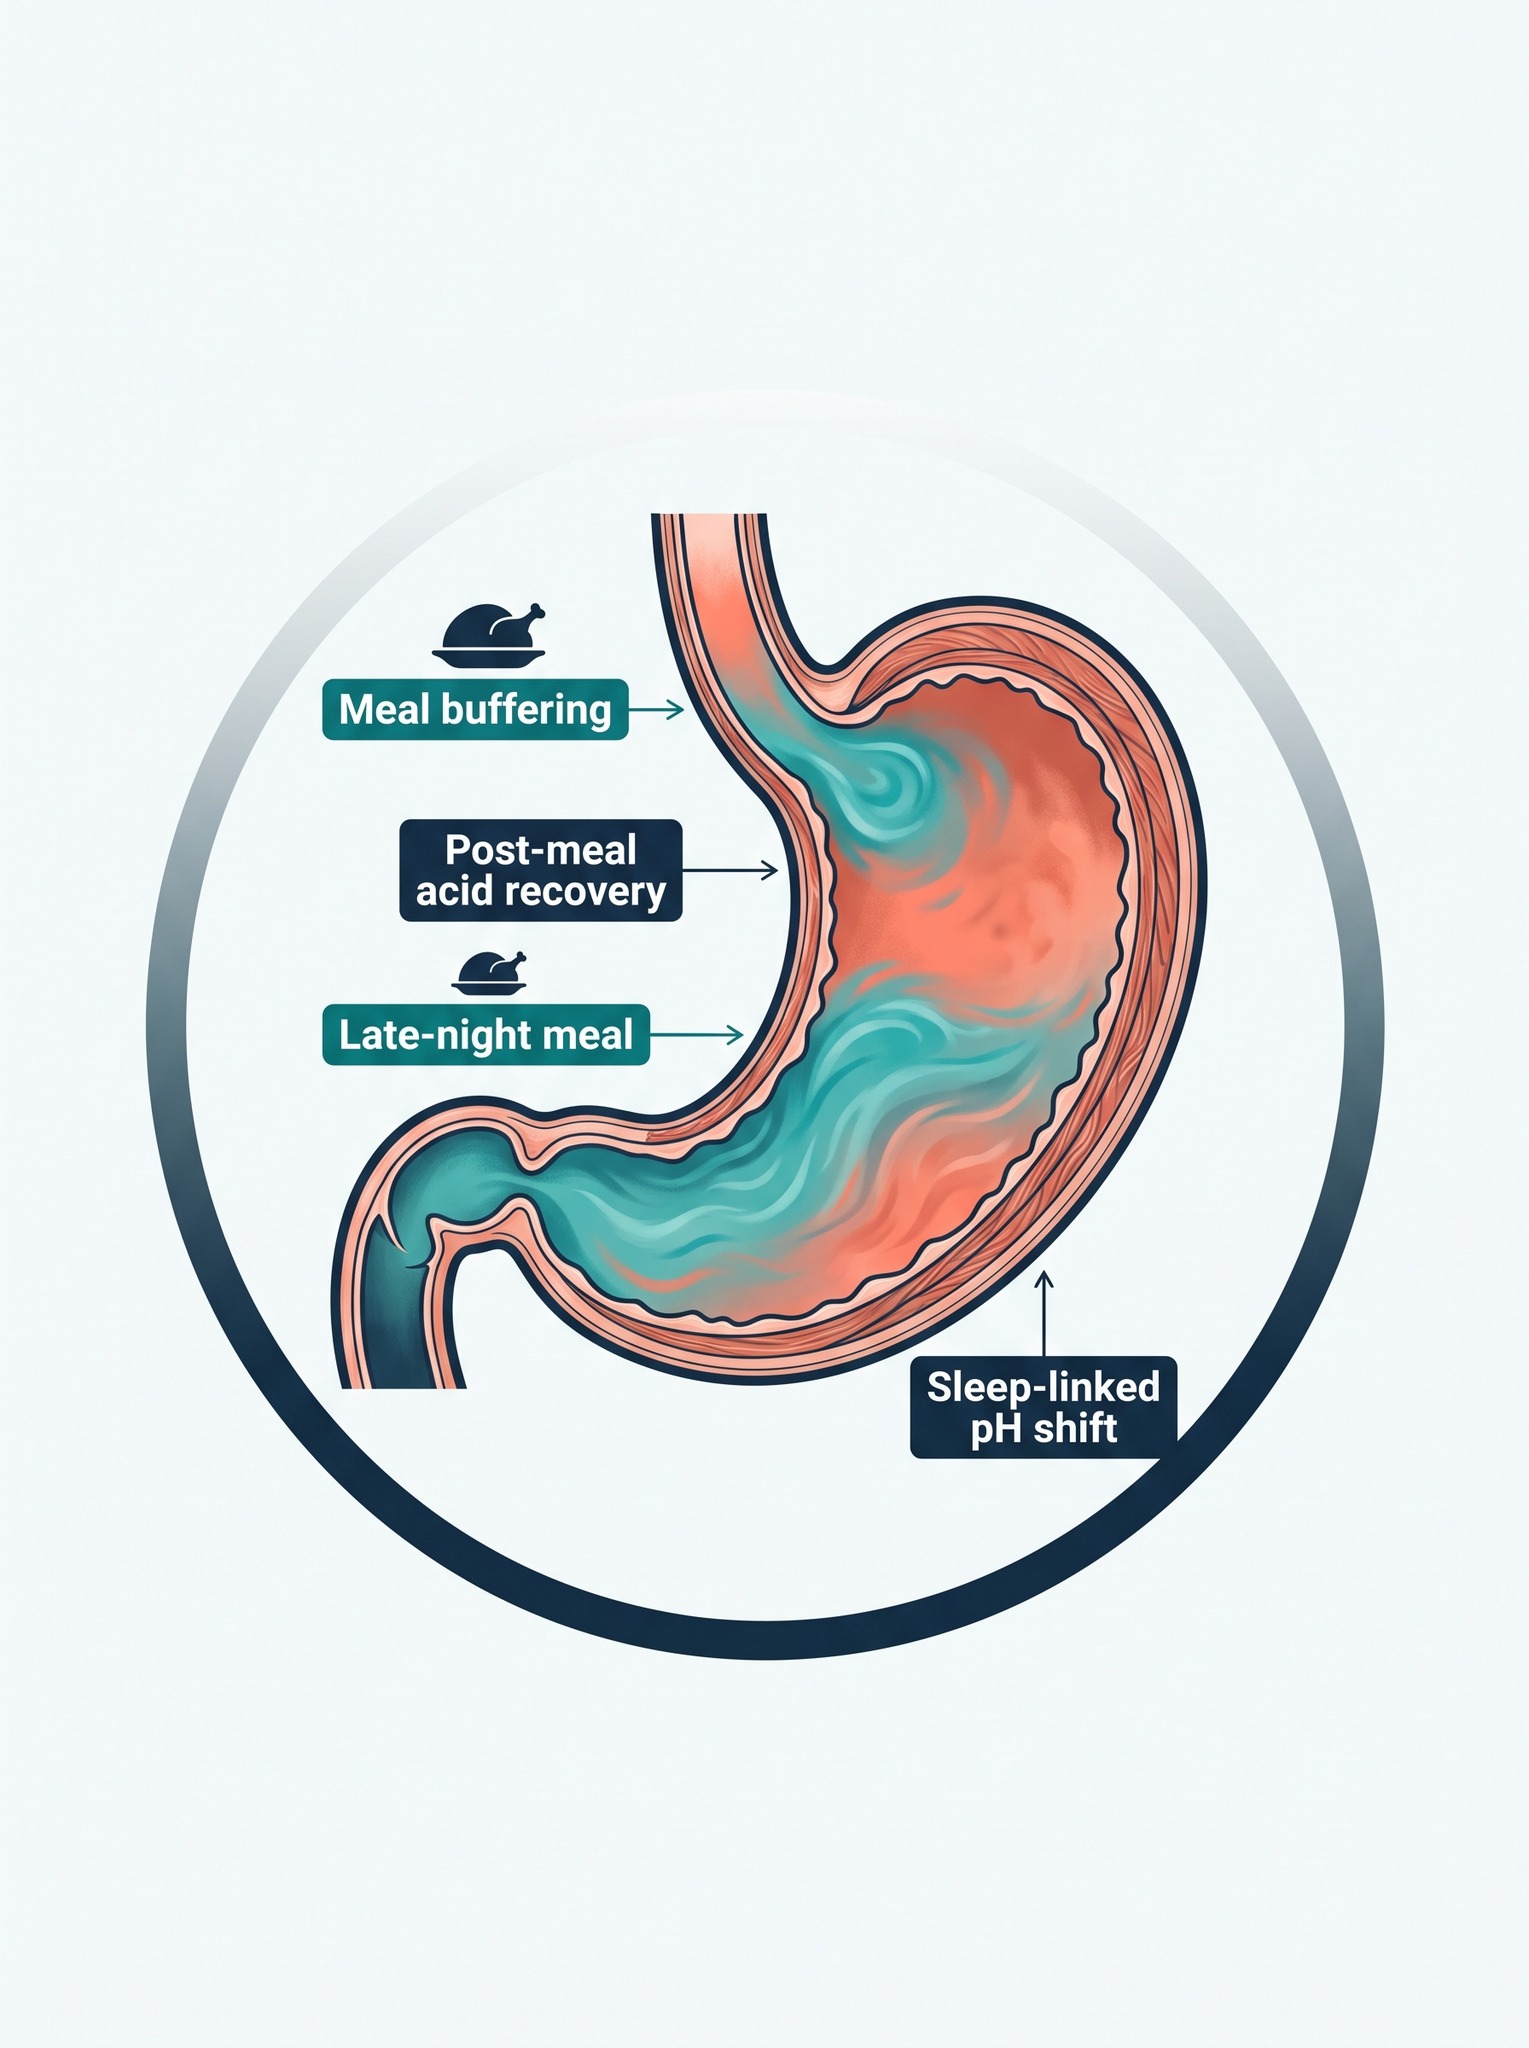
Food initially buffers stomach acid and raises luminal pH. Acid secretion then lowers the pH again while the stomach processes the meal. A late solid meal repeats this sequence close to sleep, so gastric volume and acid activity continue while Rondo is lying down. Meanwhile, his weaker supine primary wave clears retained material less efficiently.
Which hormonal signals shift with repeated late timing?
| Signal | What repeated late timing changes |
|---|---|
| Melatonin | Its circadian rise coordinates sleep with gastrointestinal motility, secretion and mucosal protection. Late light exposure and delayed sleep move that signal later, while a late meal keeps the stomach active during the same window. |
| Cortisol | Its daily low point and morning rise become less aligned with behaviour. Repeated misalignment increases autonomic arousal and visceral sensitivity, so normal gastric distension feels more painful. |
| Growth hormone | The largest pulse follows the first period of deep sleep. A delayed bedtime moves this tissue-repair signal later and short sleep reduces the deep-sleep opportunity that supports epithelial renewal. |
| Prolactin | Its sleep-linked rise also moves with delayed sleep onset. Repeated delay shifts the repair and immune-regulation window across the night, while midnight itself carries no unique biological switch. |
| Gastrin and somatostatin | These opposing signals regulate acid output. Late meals stimulate the gastrin side of the system, while chronic PPI use raises gastrin through feedback from sustained acid suppression. |
| Ghrelin and motilin | They help coordinate hunger, fasting contractions and the migrating motor complex. Repeated late eating shortens the overnight fasting interval and delays the clearance cycles that normally occur between meals. |
What did the supine study add to the explanation?
The fluoroscopic finding supplies the mechanical link. Primary peristalsis normally clears swallowed material and refluxed contents. Rondo’s primary wave weakened only when he lay down, precisely when gravity also stopped assisting clearance. A late meal therefore reaches the position in which his oesophagus performs less effectively.
Does a lifetime habit prove that the schedule fits?
“I’ve always slept late, and that’s what suits me.”
Fair enough. The stomach, inconveniently, follows circadian biology without consulting personal tradition. A familiar schedule can feel comfortable while the natural circadian rhythm, evening gastric emptying, sleep-linked hormones and Rondo’s supine clearance finding still register the physiological cost.
Why does my stomach hurt after sleeping late or poorly? I can wake with epigastric pain even when I felt little discomfort at bedtime.
Late or disrupted sleep changes several processes that determine how strongly the upper digestive tract responds to a meal. Evening solids empty more slowly, recumbency reduces gravitational clearance, and circadian misalignment changes autonomic tone, acid regulation and visceral sensitivity. Consequently, gastric distension or a short reflux episode can produce more pain, fullness or nausea. Sleep deprivation also lowers pain thresholds. Therefore, the same mechanical stimulus can generate a stronger conscious sensation after waking, especially when the lack of sleep follows late-night eating.
How closely are sleep disturbance and functional dyspepsia linked?
Sleep disorders are more common with chronic dyspeptic symptoms
Park et al., Journal of Gastroenterology and Hepatology, 2021.
Why did we recommend only one new diagnostic test?
Rondo has already had the structural questions examined from several directions. Videofluoroscopy assessed bolus transit. Endoscopy and biopsies assessed the oesophagus, stomach and duodenum. Colonoscopy, ileal biopsies and magnetic resonance enterography examined the lower digestive tract. The normal 2026 endoscopy also confirmed that active erosive disease no longer explains the continuing symptoms.
Why does the current pattern look behavior-driven?
Persistent symptoms now track sleep timing, meal timing, speed of eating and named food triggers more closely than visible tissue injury. We often see this split after mucosal healing: the camera looks reassuring, while motility and sensory signalling still reproduce the person’s symptoms. That is why the active upper-GI problem is best described as a behavior-maintained functional pattern.
How much does dinner-to-bed timing matter?
A matched study found that an interval under three hours carried 7.45 times the odds of GERD compared with an interval of at least four hours.[2] Rondo’s usual interval is about three and a half hours, yet his dinner is solid and calorie-dense, and his supine clearance is already weaker. The combined pattern matters more than the clock time alone.
Which changes address the mechanism behind the stomach pain?
Finish the final meal earlier
The final solid meal moves to 7 p.m. on four or five days each week. This creates a longer upright interval for gastric emptying and oesophageal clearance. On later days, a smaller meal reduces distension and the volume available for nighttime reflux.
Stabilize sleep near 11 p.m.
Bedtime moves toward 11 p.m. with a similar schedule across weekdays and weekends. The target supplies a repeatable relationship between food intake, darkness and sleep onset. Midnight itself carries no special switch. Consistency gives central and digestive clocks the same timing signal each day.
Remove the three repeatable food triggers
Coffee, fried onion and large cocoa portions leave the diet during the initial observation period. Coffee and chocolate reduce lower oesophageal sphincter pressure in controlled human studies.[3][4] Onion increased reflux measurements in reflux-prone participants, while frying adds a fat load that prolongs gastric retention.[5] Together, they form a mechanism-matched personal trigger set.
Regular coffee produces more oesophageal acid exposure than decaf
Pehl et al., Alimentary Pharmacology and Therapeutics, 1997.[3]
Chocolate lowered lower oesophageal sphincter pressure
Wright and Castell, American Journal of Digestive Diseases, 1975.[4]
Chew until each solid mouthful is easy to swallow
Slower chewing reduces particle size and produces a cohesive, saliva-mixed bolus. This directly answers the partial bolus retention seen when Rondo lay down. It also slows the meal itself, which reduces rapid gastric distension and the post-meal pressure that promotes reflux.
Use three minutes of diaphragmatic breathing before meals
Slow abdominal breathing shifts autonomic activity toward the parasympathetic state that supports gastric accommodation. It also recruits the diaphragmatic crura around the lower oesophageal sphincter. For a symptom pattern that began during intense stress and still worsens with fast eating, this changes the mechanical setting before the first bite.
Spread hydration and movement across the day
Water increases gradually from two glasses toward six to eight, distributed between meals. Daily moderate walking adds a regular motility signal without placing intense exercise beside a large meal. Together, these changes support gastric and bowel transit while reducing the tendency to concentrate food and fluid late in the day.
Review chronic omeprazole use without an abrupt stop
Omeprazole 40 mg has produced only partial relief, while the 2026 endoscopy shows no erosive oesophagitis, Barrett’s oesophagus or active gastric injury. That combination calls for a fresh indication review and the lowest dose that still serves a defined purpose. Chronic acid suppression also raises gastrin through feedback, which helps explain rebound acid symptoms after withdrawal. Current guidance bases deprescribing on the continuing indication and recognizes transient rebound symptoms after long-term treatment.[6] A structured step-down keeps rebound distinct from recurrent tissue damage.
What does the current vitamin B12 result mean?
His vitamin B12 is currently 540 pg/mL, within the laboratory reference range. The present priority is medication fit. The longer-term nutrient mechanism is explained separately in PPIs and vitamin B12 deficiency. The wider role of normal gastric acidity is covered in why the gut is acidic and should stay acidic.
Can stress or eating late at night cause stomach pain? Sometimes the discomfort appears that night, while on other days it is strongest the next morning.
Stress and late eating can produce the same symptom through different routes. Stress increases sympathetic activity and visceral sensitivity, which changes gastric accommodation and makes distension more painful. A late meal adds volume during a period of slower solid-food emptying and places refluxable contents close to recumbency. The effects persist into the morning when gastric clearance remains incomplete or sleep fragmentation lowers the pain threshold. Together, these mechanisms explain why symptoms can appear immediately or after waking.
Why is this mainly a behavior-maintained digestive problem?
The active upper-digestive pattern follows repeated behaviours more closely than progressive tissue injury. Symptoms track a late solid dinner, delayed sleep, fast eating and specific foods. Meanwhile, the latest endoscopy shows healed mucosa, and omeprazole has changed the symptoms only partly. This combination places motility, reflux clearance and visceral sensitivity at the centre of the current problem.
Why does the calprotectin result remain separate?
Faecal calprotectin of 289.3 μg/g is the one objective result that still needs resolution. A repeat measurement answers that question without reopening every structural investigation. If it stays high, the lower digestive tract requires renewed attention. If it normalizes, the extensive prior imaging, biopsies and normal 2026 endoscopy support the behavior-first plan even more strongly.
What changes the pattern in practice?
In our experience with similar symptom patterns, progress comes when the relevant behaviours change together and remain stable long enough for the digestive rhythm to follow. Earlier food intake reduces the nighttime mechanical load. Consistent sleep restores a repeatable circadian signal. Trigger removal reduces reflux-provoking exposures, while structured medication review prevents acid suppression from becoming the only response to every flare.
Where reflux fits into the wider pattern
The same distinction between reflux injury and persistent symptoms is explored in acid reflux without heartburn. Rondo’s case adds one unusually useful detail: the oesophagus itself showed how position changed clearance, so the daily schedule is part of the measured physiology.
Find the behaviours that keep your symptoms active
A focused assessment connects meal timing, sleep, motility, food triggers and medication use with the investigations that have already been completed.
Frequently asked questions
A bedtime after midnight becomes relevant when it accompanies late food intake, circadian delay or an inconsistent schedule. Evening solids empty more slowly, and lying down removes gravitational assistance from oesophageal clearance. The clock time therefore marks a cluster of physiological conditions. Midnight itself is simply one point on the biological night.
Endoscopy shows visible tissue structure. Functional dyspepsia can persist through altered gastric accommodation, delayed emptying, reflux clearance, visceral hypersensitivity and autonomic signalling even after erosions or inflammation have healed. A normal-looking lining and continuing symptoms describe different parts of digestive function.
Yes. Coffee and chocolate can reduce lower oesophageal sphincter pressure. Onion increased measured reflux in people with reflux symptoms, while frying adds fat that can extend gastric retention. These separate actions converge on reflux exposure, post-meal fullness and epigastric discomfort.
Long-term acid suppression raises gastrin through feedback. When the drug is withdrawn, acid output can temporarily exceed the previous level and produce heartburn, regurgitation or dyspepsia. This rebound can feel like recurrence of the original disease even when the underlying tissue remains healed.
References
- Goo RH, Moore JG, Greenberg E, Alazraki NP (1987). Circadian variation in gastric emptying of meals in humans. Gastroenterology, 93(3), 515–518.
- Fujiwara Y, Machida A, Watanabe Y, et al. (2005). Association between dinner-to-bed time and gastro-esophageal reflux disease. The American Journal of Gastroenterology, 100(12), 2633–2636.
- Pehl C, Wendl B, Pfeiffer A, Schmidt T, Kaess H (1997). The effect of decaffeination of coffee on gastro-oesophageal reflux in patients with reflux disease. Alimentary Pharmacology and Therapeutics, 11(3), 483–486.
- Wright LE, Castell DO (1975). The adverse effect of chocolate on lower esophageal sphincter pressure. The American Journal of Digestive Diseases, 20(8), 703–707.
- Allen ML, Mellow MH, Robinson MG, Orr WC (1990). The effect of raw onions on acid reflux and reflux symptoms. The American Journal of Gastroenterology, 85(4), 377–380.
- Targownik LE, Fisher DA, Saini SD (2022). AGA Clinical Practice Update on De-Prescribing of Proton Pump Inhibitors. Gastroenterology, 162(4), 1334–1342.