Yes, losing the gallbladder raises the risk of fatty liver. Bile then flows into the gut around the clock, gut bacteria shift, and the stomach acid barrier weakens. Mike, 68, feels that chain as bloating, reflux, and loose stools. In a Korean study of nearly 19,000 adults, fatty liver after gallbladder removal appeared at a 1.5-fold higher rate than in matched controls. Each link in that chain matches a symptom or a habit in Mike's week.
The gut side of life after surgery
IBSyncrasy explains how bile acids, gut bacteria, and food triggers drive IBS symptoms after cholecystectomy, and where a step-by-step plan starts. Buy IBSyncrasyWho is Mike and what brings him to us?
Mike, 68 years old
Mike is 168 cm tall and weighs 75 kg, a BMI of 26.6. He drinks about ten glasses of water a day and exercises seven days a week. He also has fatty liver, a tubular adenoma found on colonoscopy, and raised ferritin, and he takes citalopram daily.
Bloating, reflux, and diarrhea
Mike has had digestive complaints since youth, including two-day bouts of diarrhea. At least once a year, severe pain and bloating come together with diarrhea and strong reflux. Stress speeds up his bowels, and about one loose stool a week remains. An older stool test showed few probiotic bacteria, Candida, and very low secretory IgA.
One operation, two organs
Diverticulitis in 2013 brought antibiotic courses about every two months. In November 2014, Mike had a sigmoidectomy, and the surgeons removed his gallbladder during the same operation. Since then, certain foods trigger intermittent discomfort. An episode called atypical ileus began in April 2020 and recurred for four years, until obstruction surgery.
How does fatty liver after gallbladder removal develop?
The gallbladder turns a steady trickle of bile into a timed pulse. Without it, three systems lose their timing at once. The first is FGF19, a hormone released by the ileum, the last stretch of the small intestine. The second is the gut microbiome, and the third is the acid barrier that guards the small intestine. Together they raise the odds of fatty liver, known as MASLD,[1] and a person's metabolic load decides how far the process goes.
A brake loses its rhythm
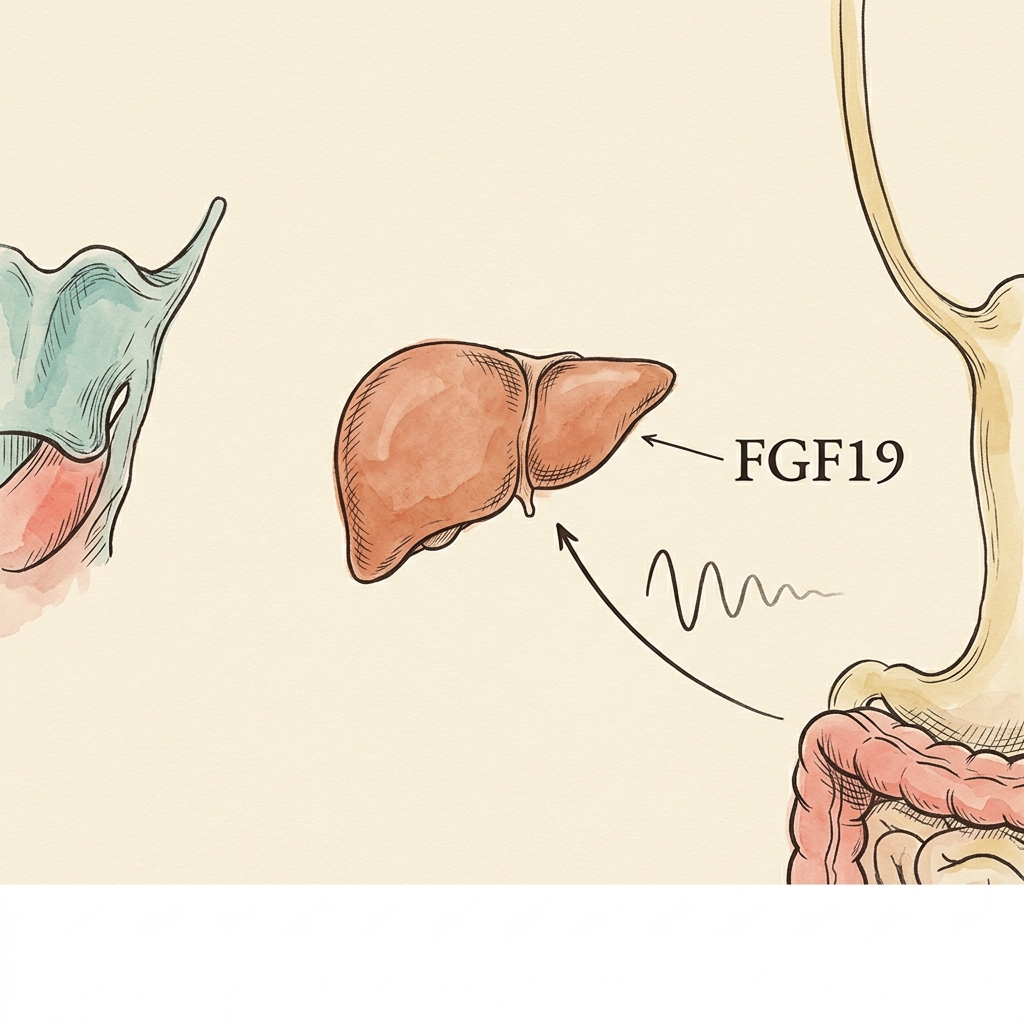
FGF19 falls by about 40%
Midday FGF19 fell about 40% within 90 days of surgery, from 1,086 to 651 pg/mL, while the liver's bile acid production at least doubled.
The gut ecosystem shifts
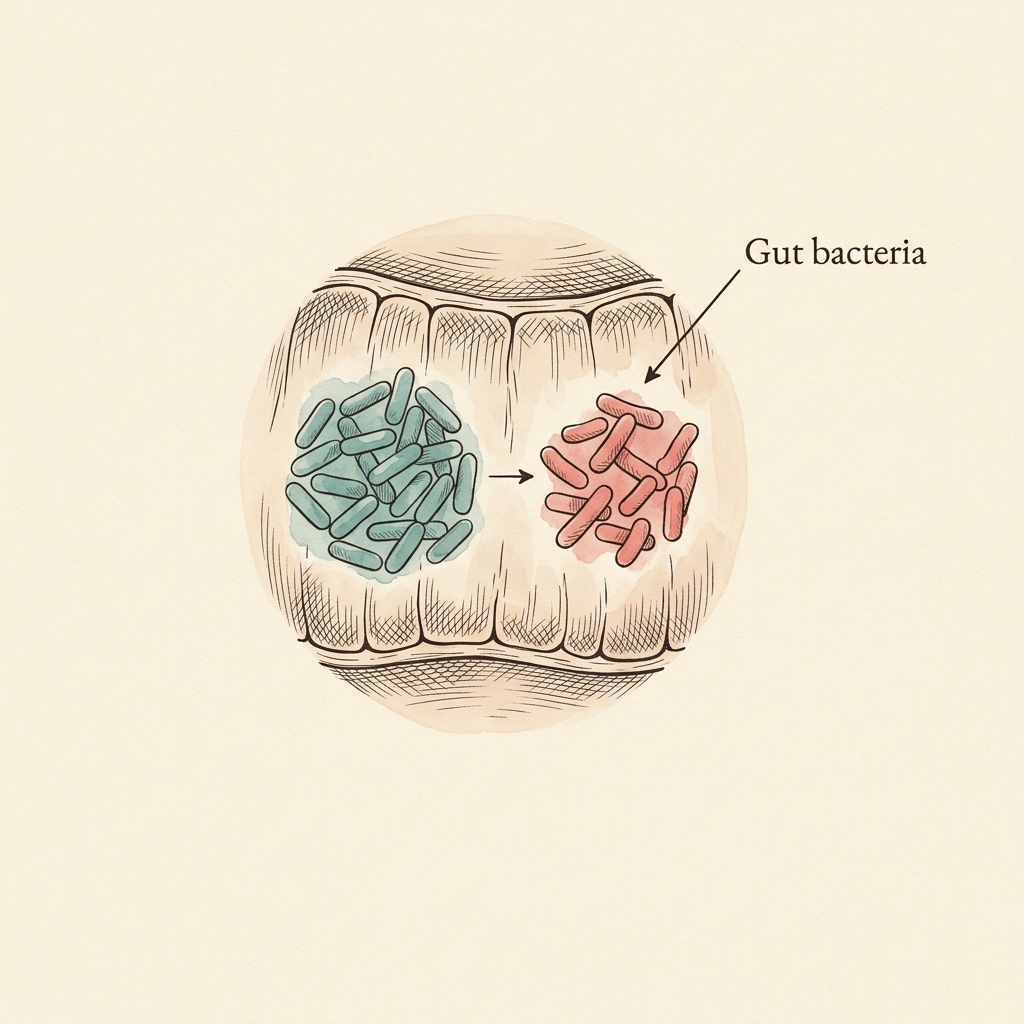
Fewer butyrate makers
After cholecystectomy, Faecalibacterium fell 14.0%, Escherichia/Shigella rose 36.7%, and LPS-producing pathways rose 35.7% in 1,968 adults.
The acid barrier opens
Bacteria hold above pH 4
Salmonella dies out below pH 3 and holds its numbers above pH 4. In a protein-meal model the stomach sits at pH 4.3 at 60 minutes, with pepsin at 5.6% of its peak.
In that Korean cohort, 4,664 patients after cholecystectomy and 13,992 matched controls were followed for 5.35 years on average. The crude hazard ratio for new MASLD reached 1.48 (95% confidence interval 1.34 to 1.64).[1] New cases appeared 48% more often at any given time.
- MASLD
- Metabolic dysfunction-associated steatotic liver disease, the 2023 consensus name for what was called non-alcoholic fatty liver disease (NAFLD). It describes fat buildup in the liver together with at least one of five metabolic risk factors. Specifically, those five are excess weight or waist size, raised fasting glucose, high blood pressure, high triglycerides, and low HDL cholesterol.
What happens to bile flow when the gallbladder is gone?
Between meals, the gallbladder stores bile and concentrates it several-fold. When fat reaches the duodenum, the hormone cholecystokinin makes the gallbladder contract, and one strong pulse of bile prepares the meal for absorption. After cholecystectomy, bile has no storage site. Thin bile then reaches the duodenum all day long through the papilla of Vater, the small opening where the duct meets the gut. As a result, every fat-rich meal meets a bile supply that stayed dilute. Mike reports food-triggered discomfort since his 2014 operation, and that timing matches this change in bile flow.
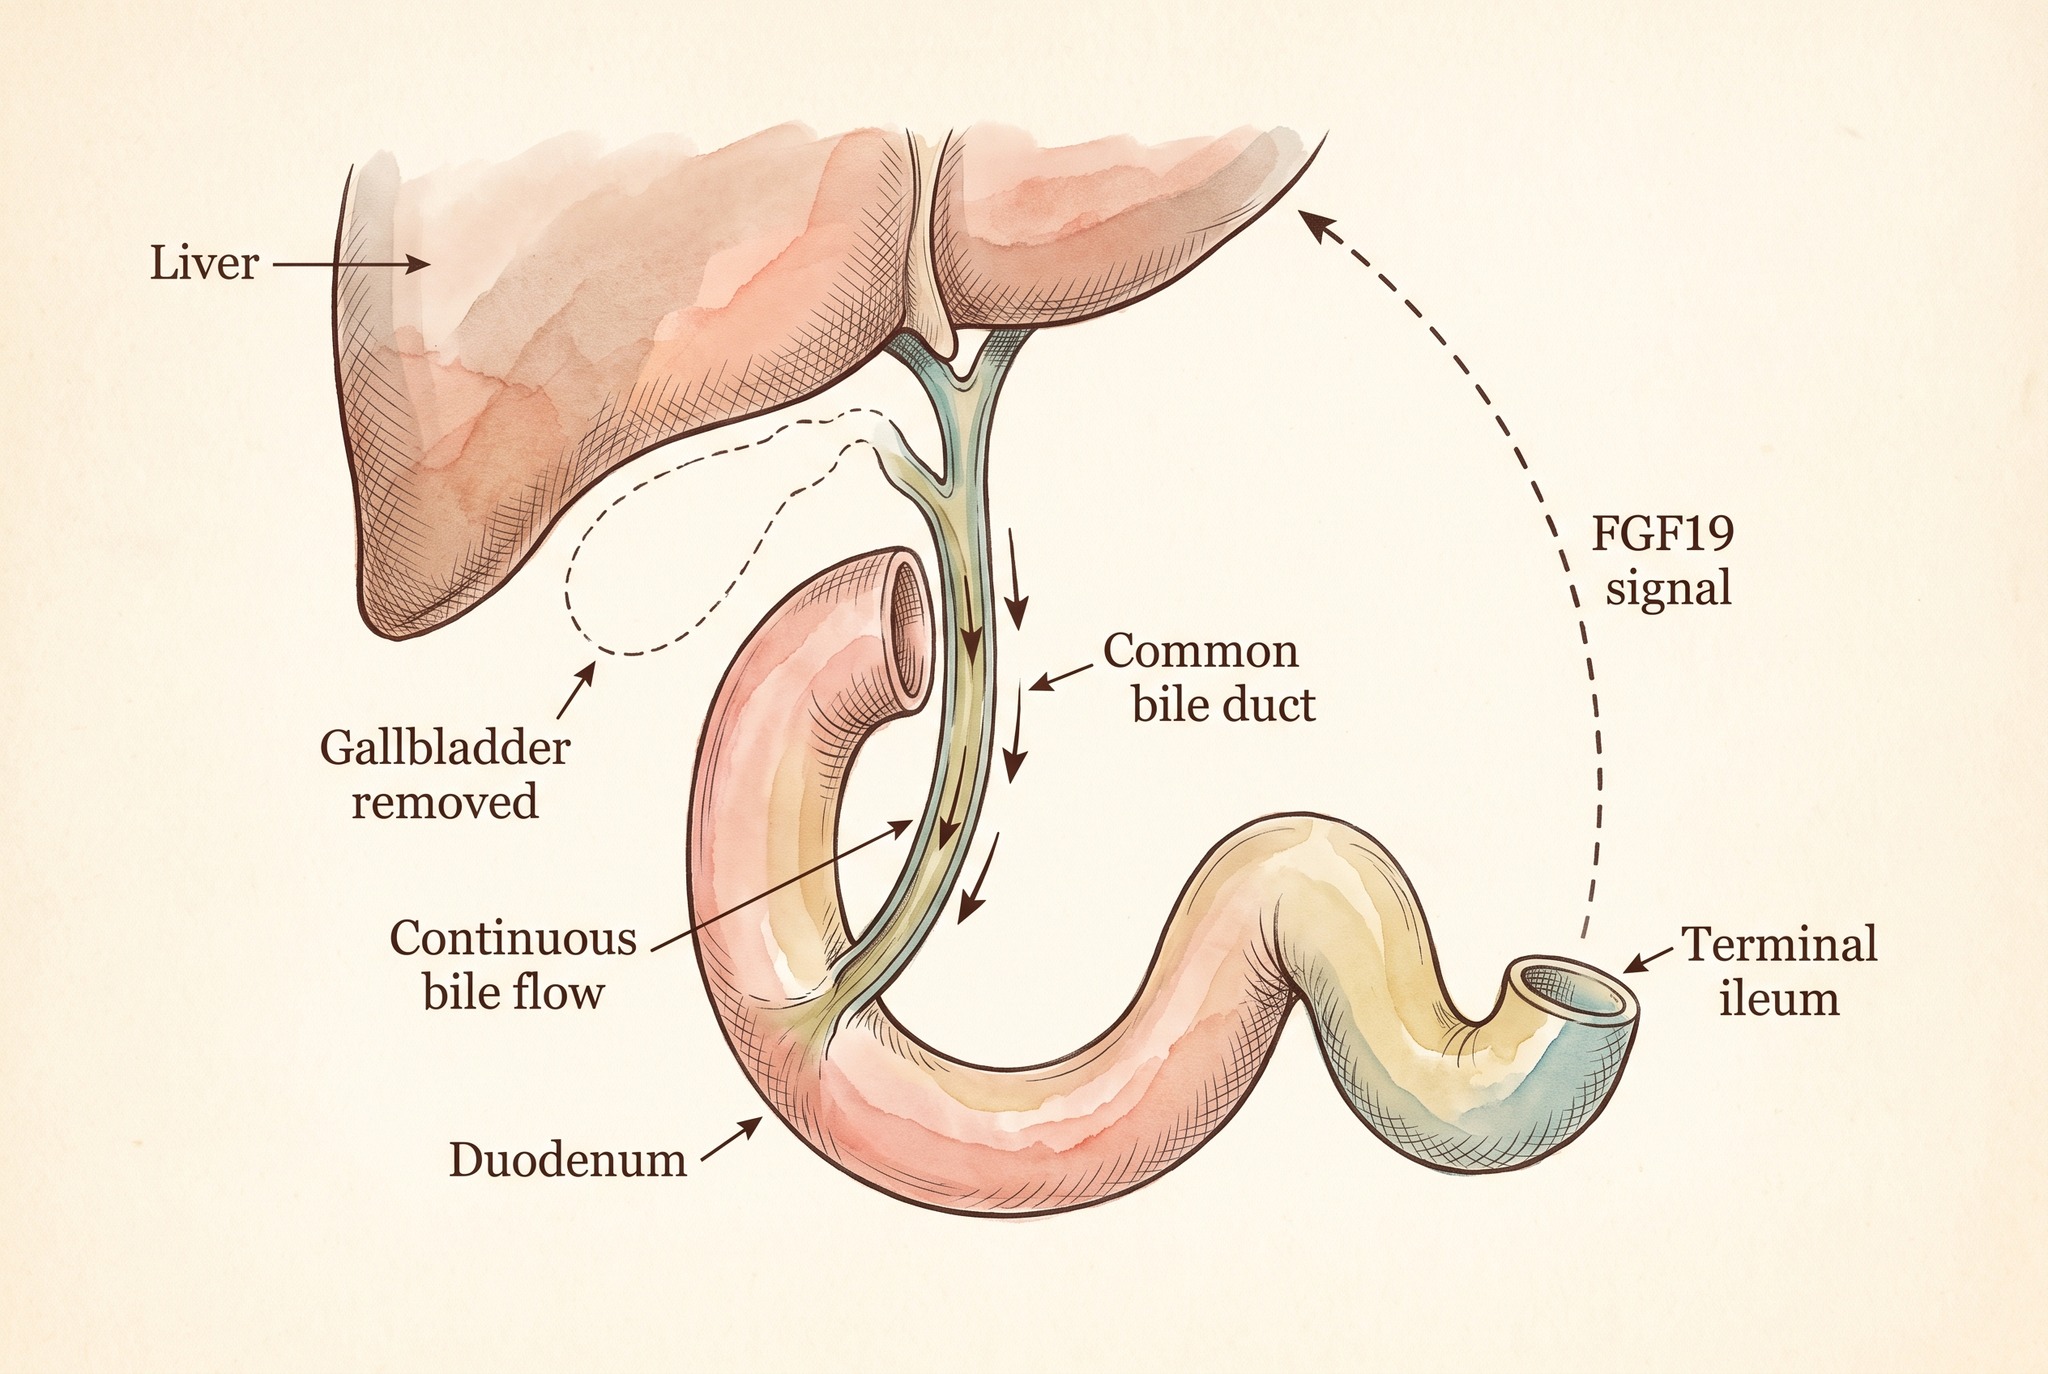
Bile that flows all day also has more chances to escape reabsorption in the ileum and reach the colon. There it stimulates the lining to secrete water and speeds stool along, so bile acid diarrhea follows. Only 202 patients (2.1%) in a multicenter audit of 9,439 laparoscopic cholecystectomies underwent the specialized retention scan (SeHCAT). Yet 127 of them, or 62.8%, had bile acid diarrhea.[2] The median wait for that scan was 672 days, almost two years. Stress speeds up transit, so less bile acid is reabsorbed, which matches Mike's stress-driven bowel and his weekly loose stool.
Why does the FGF19 brake lose its rhythm?
FGF19 (fibroblast growth factor 19) works like a brake pedal on bile acid production. The ileum releases it when bile acids arrive after a meal, and it tells the liver to slow down. The gallbladder feeds that signal as well. In 10 patients studied by Barrera and colleagues, gallbladder cells carried about 250 times more FGF19 messenger RNA than the distal ileum.[3] Likewise, gallbladder bile held about 23 times more FGF19 than serum. After surgery, midday FGF19 in the blood fell from 1,086 to 651 pg/mL within 90 days, roughly 40% lower. In the same patients, the bile acid synthesis marker C4 climbed from 33.3 to 91.2 nM at two weeks. The liver was making at least twice as much.
The brake matters for liver fat because FGF19 acts on fat metabolism too. In a 12-week trial, 82 patients with non-alcoholic steatohepatitis (NASH), the inflamed form of fatty liver, received NGM282, an engineered FGF19 analogue, or placebo. On NGM282, 74% to 79% of patients lost at least 5% of their liver fat in absolute terms, against 7% on placebo (P below 0.0001).[4] Those data show what FGF19 signaling can do for a fatty liver. The surgical data show that removing the gallbladder turns the same signal down. Mike eats his main meals at 08:00, 15:00, and 20:00, so his FGF19 signal arrives in three main waves a day. The seven-hour gap between breakfast and lunch is the longest stretch without one.
How do gut bacteria change without a gallbladder?
Bile acids shape the gut ecosystem because they act as detergents and as chemical signals for bacteria. The SHIP cohort included 1,968 adults. There, 580 people without a gallbladder carried a different microbiome from 984 controls, while 404 people with asymptomatic gallstones looked like the controls.[5] Diversity dipped slightly (Shannon index, a diversity score, 4.4 versus 4.5, P below 0.001). Faecalibacterium, a maker of the gut-protective fatty acid butyrate, fell by 14.0%, whereas Escherichia/Shigella rose by 36.7%.
These shifts also change what the microbiome produces, since predicted lipopolysaccharide (LPS) biosynthesis pathways were 35.7% more abundant after cholecystectomy (q = 0.032).[5] LPS is the outer-wall molecule of gram-negative bacteria, and small amounts cross the gut lining and travel to the liver through the portal vein. Once there, LPS switches on inflammatory signaling and promotes fat storage in liver cells. Our guide on treating gut dysbiosis in the right order covers the rebuilding.
How does stomach pH guard the small intestine?
The stomach is the first barrier against swallowed bacteria, and its strength depends on pH. Martinsen and colleagues reviewed laboratory data on bacterial survival at different pH values. Salmonella strains died out below pH 3 and held their numbers above pH 4, while diarrhea-producing E. coli declined below pH 3.5.[6] Pepsin, the enzyme that starts protein digestion, follows the same curve. In a dynamic stomach model fed a whey protein meal, the pH still sat at 4.3 after 60 minutes. Pepsin activity was 5.6% of its maximum at that point. By 90 minutes, the pH fell to 2.7 and pepsin reached 56.1%.[7]
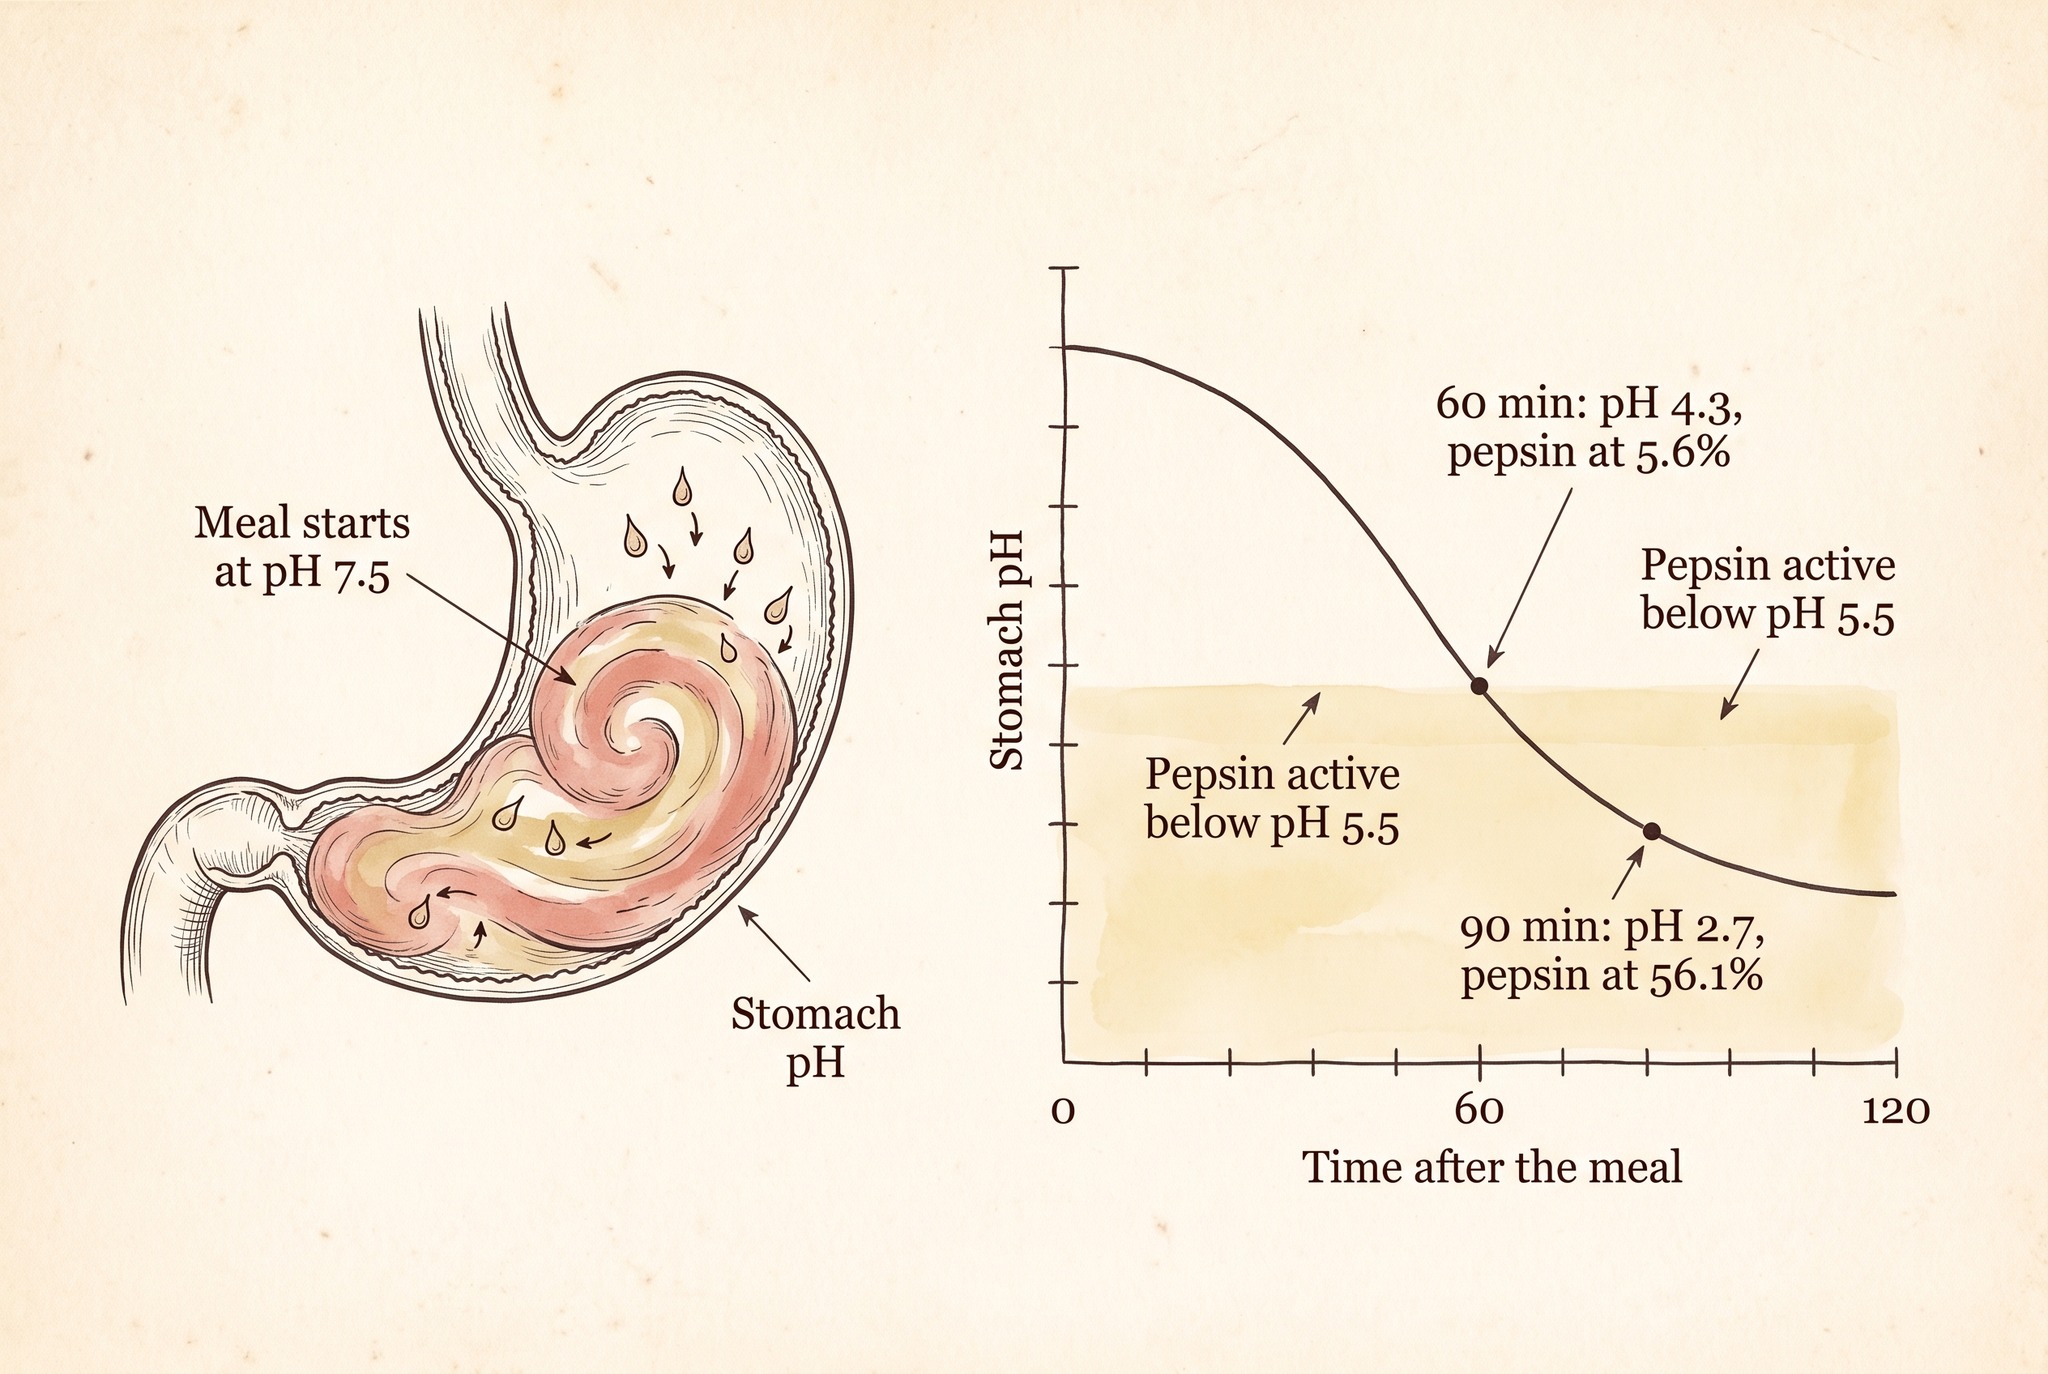
Mike drinks about ten glasses of water a day. Every glass taken around a meal dilutes acid that has to reach pH 3 or lower. Big fluid volumes also stretch the stomach, and stretching triggers the sphincter relaxations that let acid climb into the esophagus. In Mike, the dilution effect matches his bloating, and the stretch effect matches his strong reflux.
How does SIBO link the gut to the liver?
The second barrier sits in the duodenum, where bile keeps bacterial counts in check. Once bile arrives as a constant trickle, that barrier loses part of its strength, and bacteria that pass the stomach settle in the small intestine. In a Korean study, 46.8% of post-cholecystectomy patients had small intestinal bacterial overgrowth (SIBO) on a glucose hydrogen breath test.[8] By comparison, 26.2% of patients with functional gut disorders and 13.3% of healthy people tested positive (P = 0.010). Cholecystectomy was the only independent predictor, with an odds ratio of 2.35 (95% CI 1.24 to 4.48), which means more than twice the odds.
SIBO on a glucose hydrogen breath test
Percent of each group testing positive, on a 0 to 50% scale. Source: Sung HJ et al., J Neurogastroenterol Motil 2015 (glucose hydrogen breath test, P = 0.010).
SIBO is also common in fatty liver. A meta-analysis of 34 case-control studies found SIBO in 43.0% of people with MASLD.[9] Across chronic liver diseases as a group, the odds ratio for SIBO was 6.7 (95% CI 4.6 to 9.7) compared with controls. Overgrown bacteria produce more LPS and more fermentation products in the small intestine. Both then flow to the liver through the portal vein. Our guide on SIBO after gallbladder removal covers the SIBO side in more depth.
Why does the metabolic load decide the outcome?
The same Korean cohort was sorted by how many of the five metabolic risk factors each person carried.[1] The reference group had no surgery and fewer than three factors. Against that group, patients with cholecystectomy and three or more factors had a hazard ratio of 5.26 (95% CI 2.35 to 11.78). The figure is adjusted for other differences between the groups. In contrast, people with three or more factors and an intact gallbladder reached 1.65 (0.82 to 3.31), a range that includes 1.0. Patients with cholecystectomy and fewer than three factors, however, showed no measurable added risk (0.57, 0.11 to 2.35).
Adjusted hazard ratio for new MASLD
Logarithmic axis from 0.5 to 16, reference line at 1.0, and the lower bound 0.11 cut at the axis edge. Reference group: no cholecystectomy and fewer than 3 risk factors. Source: Jeon HJ et al., Sci Rep 2025 (model 3 adjusted hazard ratios, crude ratio for all patients).
Five-year incidence of MASLD followed the same order, reaching 17.1% in patients with cholecystectomy and three or more factors.[1] In contrast, with an intact gallbladder and the same load, it was 12.5%. After cholecystectomy with fewer factors, it fell to 6.3%, and the lowest-risk group had 3.9%. Mike's BMI of 26.6 already meets one of the five criteria. The start date of his fatty liver is unknown, so the tests below check each link on its own.
How do these links line up with Mike's symptoms?
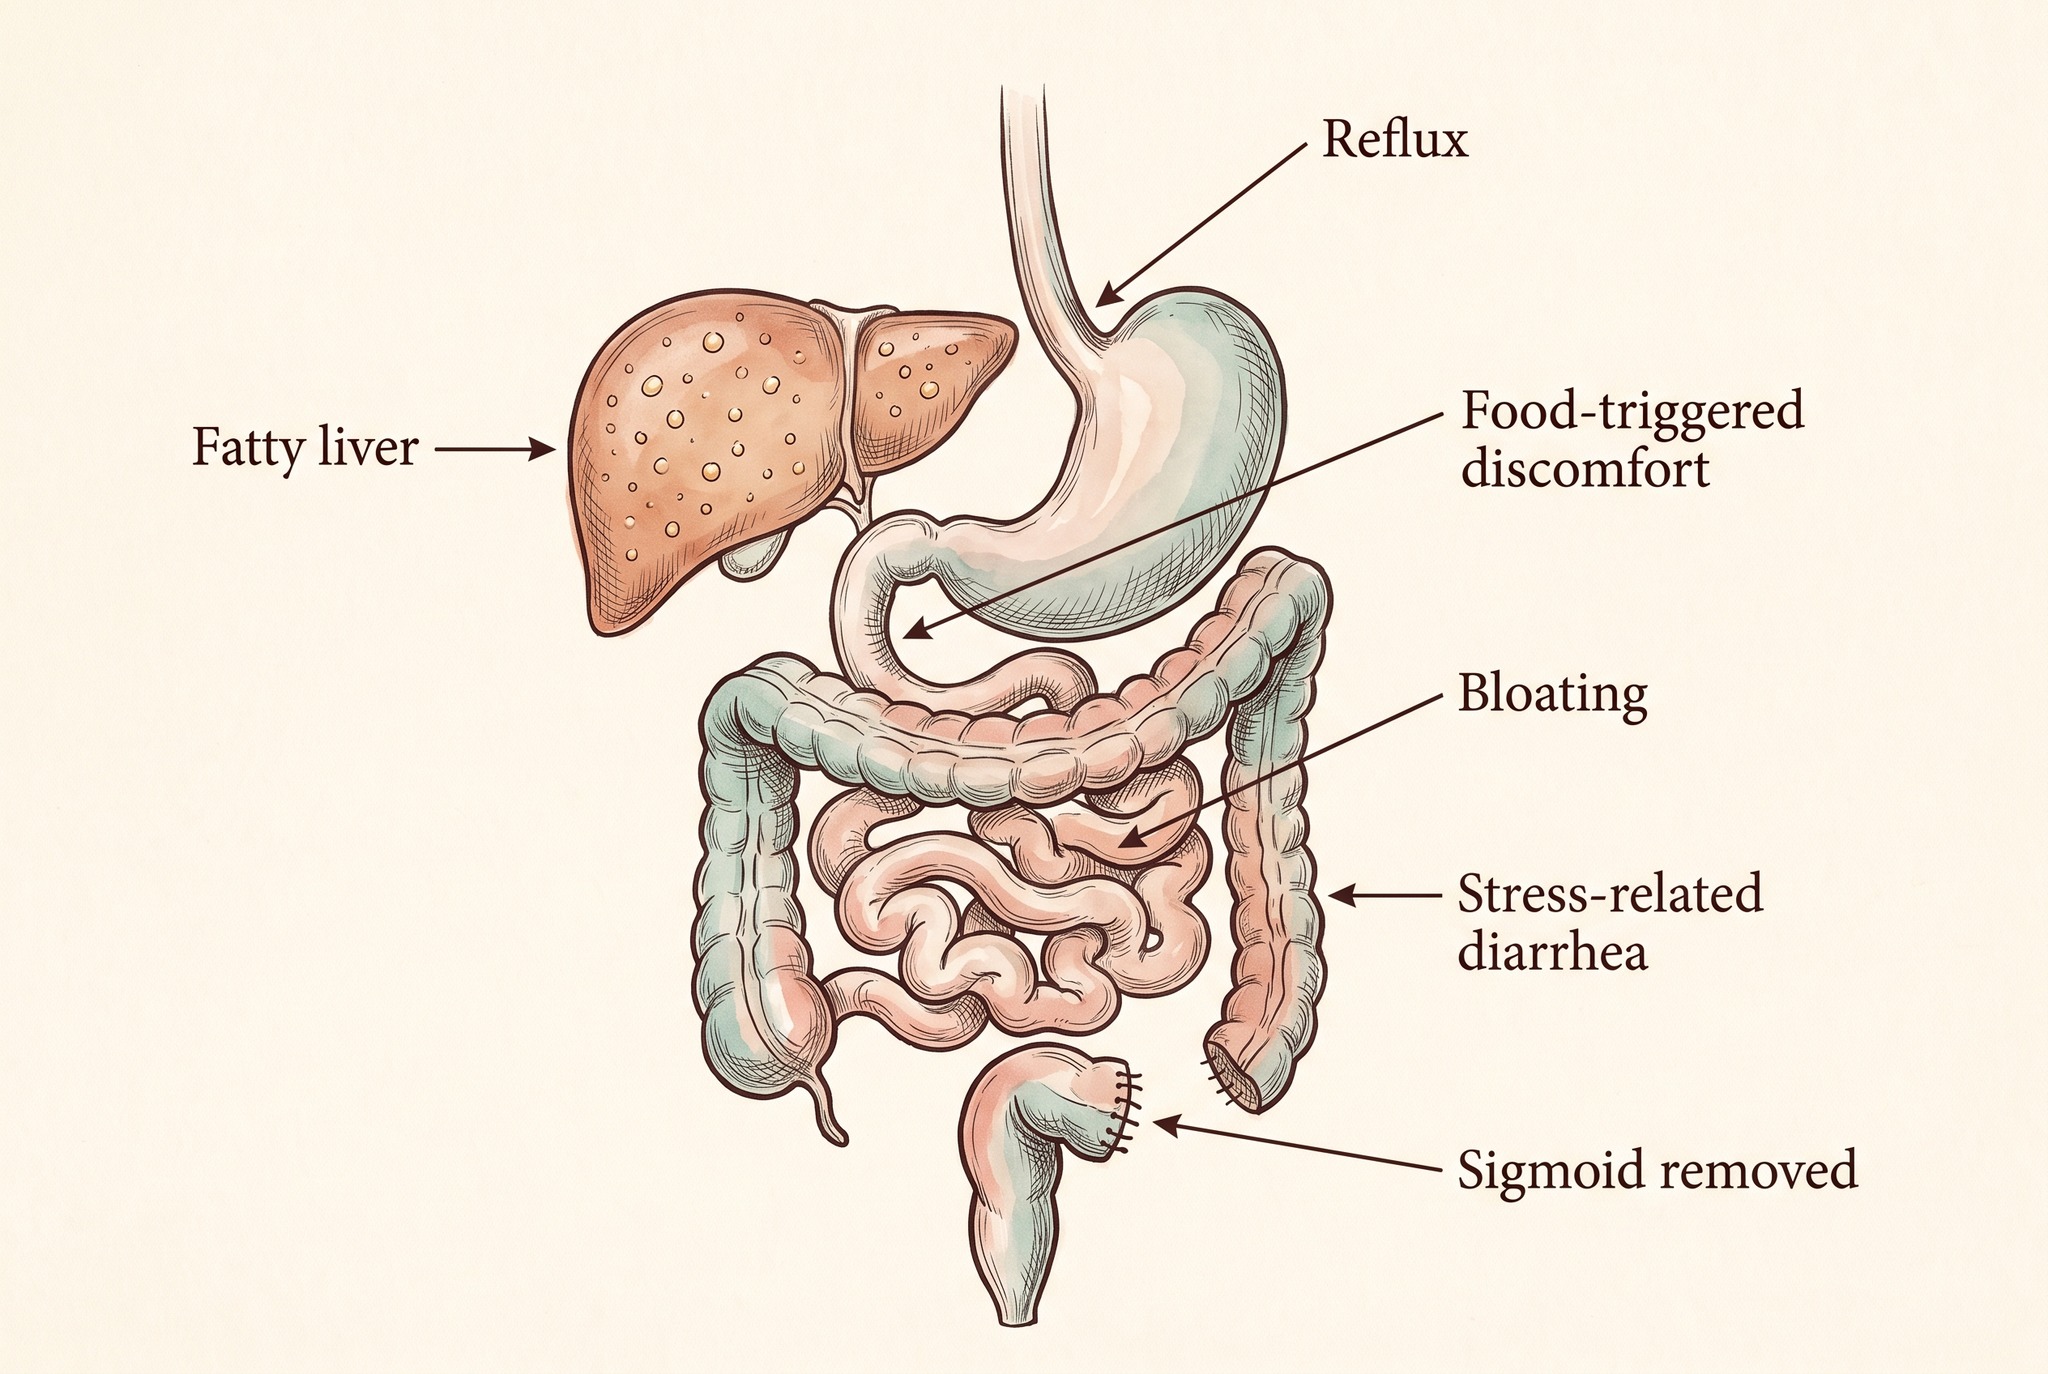
| Mike's pattern | Link in the chain |
|---|---|
| Food-triggered discomfort since the 2014 operation | Bile flows continuously, and each fat-rich meal meets a dilute supply while bile acid synthesis more than doubles.[3] |
| Three main meals a day, with seven hours between breakfast and lunch | Three main FGF19 waves a day, and midday FGF19 runs about 40% lower after surgery.[3] |
| Bloating, strong reflux, and about ten glasses of water a day | A diluted acid barrier (pH 4.3 at 60 minutes of a protein-rich meal) and SIBO in 46.8% of post-cholecystectomy patients.[7][8] |
| Stress-driven bowel and one loose stool a week | Bile acids reaching the colon, confirmed in 62.8% of the patients tested after cholecystectomy.[2] |
Which tests do we propose for Mike?
We propose 30 tests in seven groups. They cover nutrient absorption, inflammation, and metabolic load, the areas that the links above change.
What do we expect the tests to show?
Transferrin saturation separates two readings of Mike's high ferritin. A normal saturation with high ferritin points to fat and inflammation in the liver, since ferritin rises with both. A saturation above the normal range points to iron overload. Low vitamin D, B12, zinc, or magnesium would mark absorption trouble in the upper gut. Bile and bacteria decide how well the small intestine takes up those nutrients, so low values would point back to the same links.
A raised fecal calprotectin would place inflammation in the bowel wall. A low HDL with a high LDL would point to the metabolic side. At MedCaseStudies, we read all 30 values together, because one number rarely explains a mechanism with several steps. The same bile and bacteria changes also drive IBS symptoms after surgery, and our guide on IBS after gallbladder removal covers them.
I had my gallbladder removed a few years ago, and my latest ultrasound shows a fatty liver. Before the surgery, my liver looked normal. Can having your gallbladder removed lead to fatty liver?
Yes. In a Korean cohort of 4,664 patients after cholecystectomy and 13,992 matched controls, new-onset MASLD occurred at a 1.48-fold higher rate.[1] The excess concentrated in people with three or more metabolic risk factors, where the adjusted hazard ratio reached 5.26. Three changes connect the surgery to liver fat. In 10 patients, midday FGF19 fell by about 40% within 90 days while bile acid synthesis more than doubled.[3] Gut bacteria shift toward more LPS production.[5] Small intestinal bacterial overgrowth (SIBO) appears in 46.8% of patients after gallbladder removal, against 13.3% of healthy controls.[8]
Which recommendations follow from these findings?
Liquid-free meals and 60 minutes afterward for a stronger acid barrier
Liquid-free meals and a 60-minute wait afterward are recommended because gastric acid is at its weakest in the first hour after eating. In a protein-meal model, the pH sat at 4.3 after 60 minutes and fell to 2.7 by 90 minutes.[7] Pepsin activity also rose from 5.6% to 56.1% of its maximum over the same 30 minutes. Salmonella dies out below pH 3 and holds its numbers above pH 4, so the acid barrier works only once the pH has dropped.[6] Every glass of fluid in that first hour adds volume and dilutes the acid, so the pH stays higher for longer. Large volumes also stretch the stomach and trigger sphincter relaxations that let acid climb into the esophagus. A daily intake of about ten glasses of water fits into the hours between meals.
A weaker acid barrier lets more bacteria into the small intestine, and there the second barrier, bile, already runs on a constant trickle. Bacteria that settle there ferment food and release gas, so they add to bloating and reflux. The Korean breath-test study shows how common this is after surgery.[8]
Dairy three times a week for less lactose fermentation
Cutting dairy from seven servings a week to three is recommended because lactose that escapes digestion ferments in the gut and produces gas. With SIBO, however, that fermentation starts in the small intestine. Gas then adds to bloating, and our guide on the causes of abdominal bloating covers the other sources. The same fermentation also drives loose stools. On the three dairy days, plant milk, sheep cheese, and goat yogurt are the recommended choices.
Weight loss from 75 to 70 kg in two months for a lower metabolic load
A loss from 75 to 70 kg over two months is recommended because it equals 6.7% of body weight. In a 52-week study of 293 patients with biopsy-proven NASH, the effect grew with each step of weight loss. Steatohepatitis resolved in 58% of patients who lost at least 5% of their body weight, and in 90% of those who lost at least 10%.[10] A BMI of 26.6 therefore becomes 24.8 at 70 kg, below the overweight cutoff of 25. Excess weight is also one of the five metabolic risk factors that separated the 0.57 and 5.26 hazard ratios in the Korean cohort.[1]
Steatohepatitis outcomes by weight loss at 52 weeks
Percent of patients. NAS is the NAFLD activity score from liver biopsy. Source: Vilar-Gomez E et al., Gastroenterology 2015 (293 patients with biopsy-proven NASH, 52 weeks of lifestyle change).
The NAFLD activity score (NAS) grades fat, inflammation, and swelling of liver cells on a biopsy, so a lower score means less of all three. Fibrosis regressed in 19% of all patients and in 45% of those who lost at least 10%.[10] Limiting chocolate to three times a week, ideally before exercise, is also recommended because it trims added sugar and saturated fat. One weekly session to muscular failure is recommended too, because skeletal muscle is the body's largest consumer of blood glucose.
Six basic rules after cholecystectomy for reflux, fat load, and alcohol
Six basic rules are recommended after cholecystectomy because the operation changes how bile reaches each meal. Raising the head of the bed and staying upright for two hours after eating keep stomach contents and acid down. Loose clothing also keeps pressure off the abdomen. Keeping the fat in each meal small also matches a bile supply that now arrives continuously. Limiting alcohol to two drinks reduces the fat-building load on a liver that already stores fat. Finally, a 19:00 food cutoff, one hour earlier than the current 20:00 dinner, lengthens the overnight fast.
Silymarin in three-month cycles for antioxidant support of the liver
Silymarin is recommended because it is the active extract of milk thistle seed and has antioxidant activity in liver cells. For that reason, it supports the weight and meal changes in a liver with fatty infiltration. The cycle is daily use for three months, followed by a three-month pause.
Colon Life before breakfast for the loss of butyrate producers
Colon Life is recommended, one capsule before breakfast for two months, because a sigmoidectomy reduces the bacteria that produce butyrate. Butyrate is a fatty acid that fuels the cells lining the colon. The SHIP cohort showed a similar loss after cholecystectomy, since Faecalibacterium, a main butyrate maker, fell by 14.0%.[5]
Colostrum with breakfast and dinner for very low secretory IgA
Colostrum is recommended because the older stool test showed very low secretory IgA (sIgA), the antibody layer that protects the gut lining. Low sIgA means a weaker immune response against bacteria, which matters because bacterial overgrowth and LPS are two links of the mechanism above. Colostrum, the first milk of mammals, carries immunoglobulins and growth factors. For that reason, the recommendation is one capsule with breakfast and one with dinner.
How do these recommendations help the liver and gut?
How do the meal and drink recommendations help?
Each recommendation acts on one link of the chain. Liquid-free meals keep the stomach acid at working strength, so the acid barrier holds longer. The dairy reduction lowers the lactose that SIBO ferments into gas. An earlier last meal also lengthens the overnight fast. As a result, fewer bacteria settle in the small intestine, and less LPS reaches the liver.[8][5] Changes in bloating and reflux show the effect early, and the follow-up tests then confirm whether the chain has shifted.
How do the weight and supplement recommendations help?
Weight loss acts on metabolic load, the factor that separated a 5.26 hazard ratio from a 0.57 in the Korean cohort.[1] In the biopsy study, 58% of patients who lost 5% or more resolved steatohepatitis.[10] The recommended loss of 6.7% therefore sits above that threshold. Silymarin adds antioxidant activity in liver cells. Colon Life targets the butyrate producers that fuel the colon lining, while colostrum supports the gut's immune barrier, where secretory IgA is very low.
My ultrasound shows a fatty liver, and my gallbladder was removed years ago. My doctor talks about weight and diet, but I wonder whether the surgery changes what works. How do you treat a fatty liver after gallbladder removal?
Treatment of liver fat after gallbladder removal follows the standard MASLD pathway, and weight loss carries the strongest evidence. In 293 patients with biopsy-proven NASH, losing at least 5% of body weight resolved steatohepatitis in 58%. Losing at least 10% did so in 90%, and fibrosis regressed in 45%.[10] Drug options now include resmetirom, approved by the FDA in 2024, and semaglutide, approved in August 2025, both for MASH with moderate to advanced fibrosis. FGF19 analogues also reduced liver fat in a 12-week phase 2 trial.[4]
Your digestion after surgery has a measurable pattern
We look at bile flow, gut bacteria, the acid barrier, and metabolic load together. Every result then gets a next step, as it does for Mike.
Frequently asked questions
SIBO showed up in 46.8% of post-cholecystectomy patients on a glucose hydrogen breath test. The rate was 26.2% in patients with functional gut disorders and 13.3% in healthy people. Cholecystectomy was also the only independent predictor, with an odds ratio of 2.35.
In a multicenter audit of 9,439 laparoscopic cholecystectomies, 202 patients (2.1%) underwent the SeHCAT retention scan, and 127 of them (62.8%) had bile acid diarrhea. The median wait for the scan was 672 days after surgery.
Yes. In 1,968 adults from the SHIP cohort, people without a gallbladder showed slightly lower diversity than controls. They also carried 14.0% less Faecalibacterium and 36.7% more Escherichia/Shigella. Predicted LPS biosynthesis pathways rose by 35.7%.
In 293 patients with biopsy-proven NASH followed for 52 weeks, weight loss of at least 5% resolved steatohepatitis in 58% of them. It also lowered the NAFLD activity score in 82%. A loss of at least 10% resolved it in 90% and lowered the score in 100%.
Five factors count toward MASLD: excess weight or waist size, raised fasting glucose, high blood pressure, high triglycerides, and low HDL cholesterol. Patients with a cholecystectomy and three or more of them had an adjusted hazard ratio of 5.26. For comparison, the reference group had no surgery and fewer than three factors.
References
- Jeon HJ, Eun HS, Rou WS, Kim SH, Lee BS, Ahn S-K (2025). Association between cholecystectomy and the risk of new-onset metabolic dysfunction-associated steatotic liver disease: a risk-stratified cohort study. Scientific Reports, 15, 28223.
- Farrugia A, Attard JA, Hanmer S, et al. (2021). Rates of Bile Acid Diarrhoea After Cholecystectomy: A Multicentre Audit. World Journal of Surgery, 45(8), 2447-2453.
- Barrera F, Azocar L, Molina H, Schalper KA, Ocares M, Liberona J, Villarroel L, Pimentel F, Perez-Ayuso RM, Nervi F, Groen AK, Miquel JF (2015). Effect of cholecystectomy on bile acid synthesis and circulating levels of fibroblast growth factor 19. Annals of Hepatology, 14(5), 710-721.
- Harrison SA, Rinella ME, Abdelmalek MF, et al. (2018). NGM282 for treatment of non-alcoholic steatohepatitis: a multicentre, randomised, double-blind, placebo-controlled, phase 2 trial. The Lancet, 391(10126), 1174-1185.
- Frost F, et al. (2021). Carrying asymptomatic gallstones is not associated with changes in intestinal microbiota composition and diversity but cholecystectomy with significant dysbiosis. Scientific Reports, 11, 6677.
- Martinsen TC, Fossmark R, Waldum HL (2019). The Phylogeny and Biological Function of Gastric Juice, Microbiological Consequences of Removing Gastric Acid. International Journal of Molecular Sciences, 20(23), 6031.
- Mennah-Govela YA, Swackhamer C, Bornhorst GM (2021). Gastric secretion rate and protein concentration impact intragastric pH and protein hydrolysis during dynamic in vitro gastric digestion. Food Hydrocolloids for Health, 1, 100027.
- Sung HJ, Paik C-N, Chung WC, Lee K-M, Yang J-M, Choi M-G (2015). Small intestinal bacterial overgrowth diagnosed by glucose hydrogen breath test in post-cholecystectomy patients. Journal of Neurogastroenterology and Motility, 21(4), 545-551.
- Shah A, Spannenburg L, Thite P, et al. (2025). Small intestinal bacterial overgrowth in chronic liver disease: an updated systematic review and meta-analysis of case-control studies. eClinicalMedicine, 80, 103024.
- Vilar-Gomez E, Martinez-Perez Y, Calzadilla-Bertot L, et al. (2015). Weight loss through lifestyle modification significantly reduces features of nonalcoholic steatohepatitis. Gastroenterology, 149(2), 367-378.